Severe InfluenzaAntivirals for Treatment of Severe Influenza: A Systematic Review and Network Meta-Analysis of Randomised Controlled Trials
Oseltamivir and peramivir may shorten hospital stay in severe seasonal influenza, but their effect on mortality and other critical outcomes remains uncertain on low- to very-low-certainty evidence.
Originally Published: 23 August 2024
MedED Summary Published: 24 August 2024
Author: The Medical Education Network
Catalogue Number: MICS005
Platform: www.meded.co.za
This summary is based on an open-access article distributed under the terms of the CC BY licence, which permits unrestricted use, distribution and reproduction in any medium. AI may have been used to assist in preparing this summary. The content is intended as an overview only and does not replace the original research article. Medical Education Network strongly encourages all members to review the original study before forming clinical opinions or making decisions.
Read the full open-access paper
This document is based on original research published in The Lancet:
Gao, Y., Guyatt, G., Uyeki, T. M., Liu, M., Chen, Y., Zhao, Y., Shen, Y., Xu, J., Zheng, Q., Li, Z., Zhao, W., Luo, S., Chen, X., Tian, J., & Hao, Q. (2024). Antivirals for treatment of severe influenza: a systematic review and network meta-analysis of randomised controlled trials. Lancet (London, England), 404(10454), 753–763. https://doi.org/10.1016/S0140-6736(24)01307-2
The full paper carries the complete network geometry, the GRADE certainty ratings for every comparison, and the trial-level characteristics table reproduced in part in this summary. The review is registered with PROSPERO under CRD42023456650.
Licence and attribution
This summary is based on an open-access article published under a Creative Commons Attribution (CC BY 4.0) licence, which permits unrestricted use, distribution and reproduction in any medium, provided the original work is properly cited. Copyright in the original article remains with the authors.
It is an independent interpretation prepared by the Medical Education Network and has not been reviewed or endorsed by the study authors or the publisher. Charts have been redrawn from data reported in the original article.
The summary does not replace the original research, and members are strongly encouraged to review the original study before forming clinical opinions or making decisions. Please see the Disclaimer at the end of this page for more information.
© 2024 Medical Education Network. All rights reserved.
Clinical Context and Study Purpose
Influenza typically presents with mild to moderate upper respiratory symptoms that resolve within a week. Certain populations, however — young children under five, adults aged 65 and above, pregnant women, and individuals with chronic medical conditions — carry an increased risk of developing severe illness from the infection.
In patients hospitalised with seasonal influenza, complications such as severe pneumonia, respiratory failure, multi-organ failure and secondary bacterial infection can lead to significant mortality, with case-fatality rates for adults ranging from 4% to 8%. Among immunocompromised individuals, the mortality rate can be as high as 10% to 15%. Identifying effective therapies for severe influenza is therefore essential for global public health.
Antivirals, particularly the neuraminidase inhibitors, are recommended for patients with severe influenza. Systematic reviews and meta-analyses suggest that these treatments, when administered early, may reduce mortality and shorten hospital stay. Most of that earlier work, however, focused on the relative effects of neuraminidase inhibitors alone — neglecting to assess the impact of antivirals on zoonotic influenza, or to evaluate the certainty of the evidence.
How the Evidence Was Gathered
The authors searched for randomised controlled trials published up to 20 September 2023. Trials were eligible if they enrolled hospitalised patients with suspected or confirmed influenza and compared direct-acting influenza antivirals against placebo, standard care, or other antivirals.
The systematic search covered Embase, the Cochrane Central Register of Controlled Trials, the Cumulative Index to Nursing and Allied Health Literature, Global Health, Epistemonikos and ClinicalTrials.gov.
Two coauthors independently extracted data on study characteristics, patient demographics, antiviral types and clinical outcomes, with any differences resolved by discussion or by consultation with a third coauthor.
Outcomes of interest
- Time to symptom alleviation
- Duration of hospitalisation
- ICU admission
- Progression to invasive mechanical ventilation
- Duration of mechanical ventilation
- Mortality
- Emergence of antiviral resistance
- Serious adverse events
The certainty of evidence was assessed using the GRADE (Grading of Recommendations Assessment, Development and Evaluation) approach.

Trials Included in the Review
Eight trials with 1,424 participants (mean age 36–60 years for trials that reported mean or median age; 43–78% male patients) were included in this systematic review, of which six were included in the network meta-analysis.1-8 The proportion of patients with laboratory-confirmed influenza ranged from 79% to 100%.
The interventions in the trials included oseltamivir, peramivir, zanamivir, rimantadine, zanamivir combined with rimantadine, and baloxavir combined with neuraminidase inhibitors. Three trials directly compared oseltamivir and peramivir to standard care or placebo.2,3,8
The remaining five trials compared different antivirals against each other:
- Two trials compared oseltamivir with peramivir1,5
- One trial compared oseltamivir with zanamivir7
- One compared zanamivir and rimantadine with rimantadine alone4
- One trial compared baloxavir plus neuraminidase inhibitors with neuraminidase inhibitors alone6
Standard care varied, based on local hospital protocols or the doctor's choice, and usually did not involve neuraminidase inhibitors.
Basic characteristics of the randomised controlled trials included in this systematic review
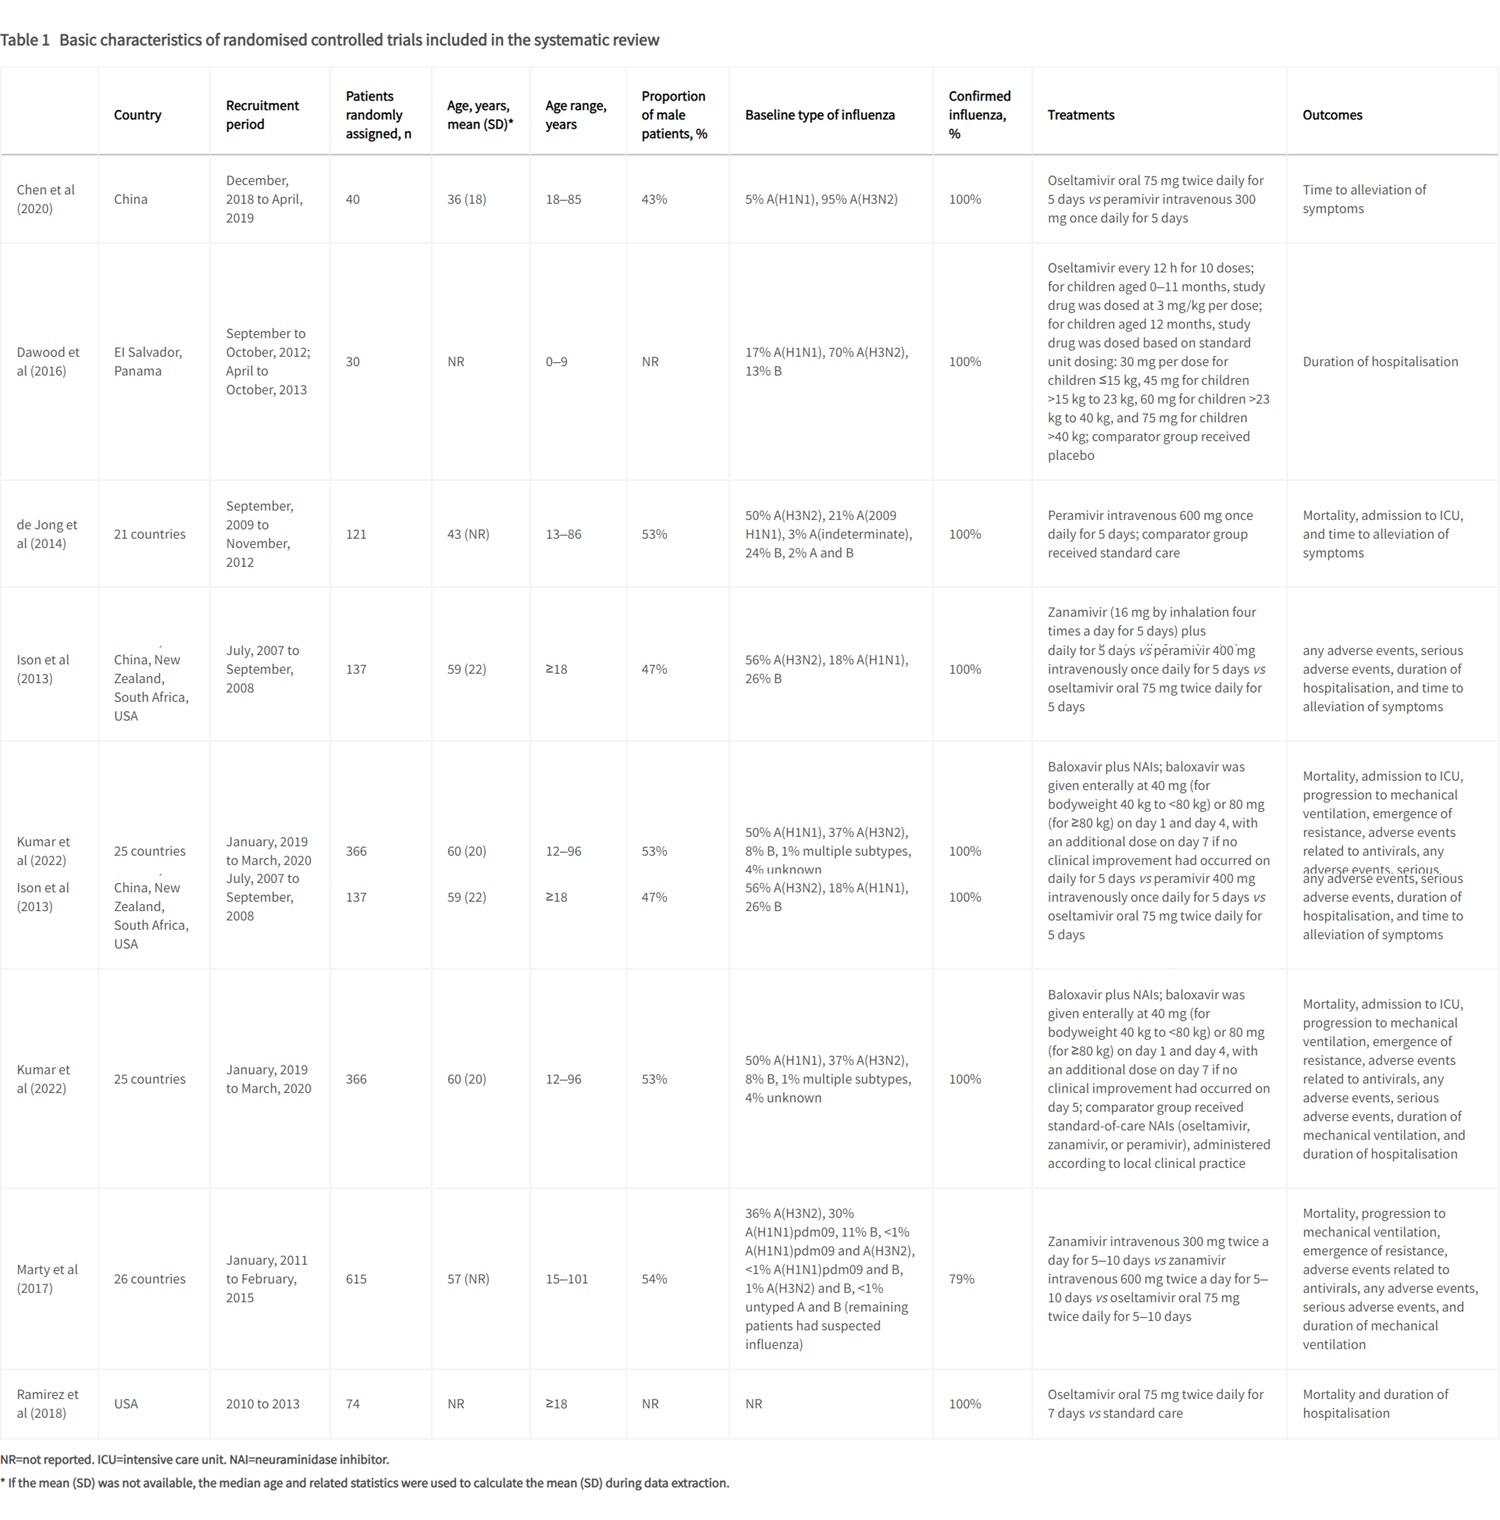
Source: Table 1 of Gao et al. (2024).
Findings
Mortality
A network meta-analysis encompassing four trials evaluated the impact of oseltamivir, peramivir and zanamivir on mortality among 813 patients with severe seasonal influenza. The findings revealed a range of risk differences, indicating that these antiviral agents could potentially decrease mortality by up to 18 fewer deaths per 1,000 patients for seasonal influenza, and by as much as 232 fewer deaths per 1,000 for zoonotic influenza. Some comparisons, however, indicated a slight increase in risk, and the certainty of this evidence remains very low.4,5,6,7,8
ICU admission
In a separate analysis focused on ICU admissions, two trials involving 235 patients with severe seasonal influenza compared the effects of oseltamivir and peramivir.3,5 The risk differences for ICU admission varied, showing 29 fewer to 43 more admissions per 1,000 patients, again with very low certainty in the evidence.
Duration of hospitalisation
Three trials, which included a total of 226 patients suffering from severe seasonal influenza, reviewed the difference in hospital stay between patients treated with either oseltamivir or peramivir. Results indicated that oseltamivir reduced hospitalisation by an average of 1.63 days compared to standard care or placebo, while peramivir led to a reduction of 1.73 days — though again, the evidence supporting these findings is classified as low certainty.2,5,8
Adverse events
Two trials involving a total of 752 patients assessed adverse events associated with oseltamivir, peramivir and zanamivir in severe influenza cases. The analysis showed no significant differences in the occurrence of either adverse or serious adverse events among the three antivirals.5,7
Mechanical ventilation and resistance
One study specifically examined the outcomes related to oseltamivir or zanamivir treatment, focusing on progression to mechanical ventilation, duration of mechanical ventilation, emergence of resistance and associated adverse events. Compared to zanamivir, oseltamivir presented relative risks ranging from 1.20 to 2.89 for these outcomes, with 95% confidence intervals overlapping the null effect. The average duration of mechanical ventilation was 0.89 days longer with oseltamivir, reinforcing the very low certainty of this evidence.7
Combination regimens
The researchers compared the combination of baloxavir and neuraminidase inhibitors to neuraminidase inhibitors alone. This study found minimal differences in hospitalisation duration (a mean difference of 0.31 days shorter) and a slight reduction in the emergence of antiviral resistance (25 fewer cases per 1,000 patients), both supported by low-certainty evidence. Very low certainty evidence also surrounded the effects of combination treatment on ICU admissions, mechanical ventilation, mortality or adverse events when compared to neuraminidase inhibitors alone.6
Finally, a single trial explored the effects of combining zanamivir with rimantadine against rimantadine alone. The evidence regarding this combination's impact on hospitalisation duration, mortality and adverse events was categorised as very low certainty.4

Interpreting the Evidence
Antivirals play a crucial role in managing severe influenza, and previous studies have suggested that early treatment with neuraminidase inhibitors may lower mortality and shorten hospital stay. Those analyses, however, focused primarily on neuraminidase inhibitors, did not address severe zoonotic influenza, and lacked an evaluation of evidence certainty. To date, no network meta-analysis has comprehensively assessed all antiviral treatments for severe influenza, leaving the optimal antiviral drug uncertain.
This study presents low-certainty evidence indicating that oseltamivir and peramivir may reduce the duration of hospitalisation for patients with severe seasonal influenza compared to placebo or standard care. Despite this, significant uncertainty remains about the impact of oseltamivir, peramivir and zanamivir on mortality rates in both seasonal and zoonotic influenza cases.
Importantly, no significant differences were found in adverse or serious adverse events among the three antivirals, although this conclusion too is based on very low certainty evidence. The effects of other antivirals such as baloxavir on mortality and other critical outcomes in severe influenza patients remain unclear.

Limitations and Conclusion
The researchers indicate that the study had a number of limitations. Only eight eligible trials were identified, with six included in the network meta-analyses, leading to uncertainty about the effects of antivirals on severe influenza outcomes.
Sparse data prevented subgroup analyses based on secondary bacterial infection or influenza type, and there was a lack of information on individuals over 60 and on children. Most trials focused on seasonal influenza, and concerns were raised about bias arising from inadequate allocation concealment and blinding. Consequently, the certainty of evidence for all comparisons was assessed as low or very low. Future trials may enhance evidence quality, prompting periodic updates to this systematic review.
References
- Chen, H. D., Wang, X., Yu, S. L., Ding, Y. H., Wang, M. L., & Wang, J. N. (2020). Clinical effectiveness of intravenous peramivir compared with oseltamivir in patients with severe influenza A with primary viral pneumonia: a randomized controlled study. Open Forum Infectious Diseases, 8(1), ofaa562. https://doi.org/10.1093/ofid/ofaa562
- Dawood, F. S., Jara, J., Gonzalez, R., Castillo, J. M., De León, T., Estripeaut, D., Luciani, K., Sujey Brizuela, Y., Barahona, A., Cazares, R. A., Lawson, A. M., Rodriguez, M., de Viana, D., Franco, D., Castillo, M., Fry, A. M., Gubareva, L., Tamura, D., Hughes, M., Gargiullo, P., … Widdowson, M. A. (2016). A randomized, double-blind, placebo-controlled trial evaluating the safety of early oseltamivir treatment among children 0–9 years of age hospitalized with influenza in El Salvador and Panama. Antiviral Research, 133, 85–94. https://doi.org/10.1016/j.antiviral.2016.07.007
- de Jong, M. D., Ison, M. G., Monto, A. S., Metev, H., Clark, C., O'Neil, B., Elder, J., McCullough, A., Collis, P., & Sheridan, W. P. (2014). Evaluation of intravenous peramivir for treatment of influenza in hospitalized patients. Clinical Infectious Diseases, 59(12), e172–e185. https://doi.org/10.1093/cid/ciu632
- Ison, M. G., Gnann, J. W., Jr, Nagy-Agren, S., Treanor, J., Paya, C., Steigbigel, R., Elliott, M., Weiss, H. L., Hayden, F. G., & NIAID Collaborative Antiviral Study Group. (2003). Safety and efficacy of nebulized zanamivir in hospitalized patients with serious influenza. Antiviral Therapy, 8(3), 183–190. https://pubmed.ncbi.nlm.nih.gov/12924534/
- Ison, M. G., Hui, D. S., Clezy, K., O'Neil, B. J., Flynt, A., Collis, P. J., Simon, T. J., & Alexander, W. J. (2013). A clinical trial of intravenous peramivir compared with oral oseltamivir for the treatment of seasonal influenza in hospitalized adults. Antiviral Therapy, 18(5), 651–661. https://doi.org/10.3851/IMP2442
- Kumar, D., Ison, M. G., Mira, J. P., Welte, T., Hwan Ha, J., Hui, D. S., Zhong, N., Saito, T., Katugampola, L., Collinson, N., Williams, S., Wildum, S., Ackrill, A., Clinch, B., & Lee, N. (2022). Combining baloxavir marboxil with standard-of-care neuraminidase inhibitor in patients hospitalised with severe influenza (FLAGSTONE): a randomised, parallel-group, double-blind, placebo-controlled, superiority trial. The Lancet Infectious Diseases, 22(5), 718–730. https://doi.org/10.1016/S1473-3099(21)00469-2
- Marty, F. M., Vidal-Puigserver, J., Clark, C., Gupta, S. K., Merino, E., Garot, D., Chapman, M. J., Jacobs, F., Rodriguez-Noriega, E., Husa, P., Shortino, D., Watson, H. A., Yates, P. J., & Peppercorn, A. F. (2017). Intravenous zanamivir or oral oseltamivir for hospitalised patients with influenza: an international, randomised, double-blind, double-dummy, phase 3 trial. The Lancet Respiratory Medicine, 5(2), 135–146. https://www.thelancet.com/journals/lanres/article/PIIS2213-2600(16)30435-0/abstract
- Ramirez, J., Peyrani, P., Wiemken, T., Chaves, S. S., & Fry, A. M. (2018). A randomized study evaluating the effectiveness of oseltamivir initiated at the time of hospital admission in adults hospitalized with influenza-associated lower respiratory tract infections. Clinical Infectious Diseases, 67(5), 736–742. https://doi.org/10.1093/cid/ciy163
Disclaimer & Fact-Checking Policy
Disclaimer. This is a summary of published research and does not replace the original study or local treatment guidelines. Every effort has been made to attribute quotes and content correctly. Where possible, all information has been independently verified. The Medical Education Network bears no responsibility for any inaccuracies which may occur from the use of third-party sources. AI may have been used to assist in preparing this summary. All efforts have been made to validate the content against the original material; however, inaccuracies may occur. The Medical Education Network urges all practitioners to review the original material as their clinical reference. The Medical Education Network bears no responsibility where these clinical summaries are used as a proxy for the original research. If you have any queries regarding this article contact us
Fact-checking Policy. The Medical Education Network makes every effort to review and fact-check the articles used as source material in our summaries and original material. We have strict guidelines in relation to the publications we use as our source data, favouring peer-reviewed research wherever possible. Every effort is made to ensure that the information contained here accurately reflects the original material. Should you find inaccuracies or out-of-date content or have any additional issues with our articles, please make use of the Contact Us form to notify us.

