- View Candida Auris: priority pathogen on the march Currently reading
Priority Fungal PathogensCandida auris: A Priority Pathogen on the March
Fungal infections have drawn a fraction of the attention given to resistant bacteria. The WHO’s first fungal priority pathogens list puts Candida auris in its critical group — and South Africa has been living with it since 2009.
Published on MedED: 17 April 2022
Type of article: Article and news review
Compiler: Linda Ravenhill
Catalogue Number: MIR001
Platform: www.meded.co.za
AI may have been used to assist in preparing this article. The content is intended as an overview only and does not replace the original sources. Medical Education Network strongly encourages all members to review the original material before forming clinical opinions or making decisions.
Where this review draws from
This article is a compiled review rather than a summary of a single study. It draws on five sources, listed in full in the References:
Bradley (JAMA, 2019) · CDC Candida auris pages (2022) · Govender et al. (Emerging Infectious Diseases, 2018) · van Schalkwyk et al. (Emerging Infectious Diseases, 2019) · the WHO fungal priority pathogens list (2022).
Attribution
This article is compiled from a variety of resources researched and compiled by the contributor. It is in no way presented as an original work. Every effort has been made to correctly attribute quotes and content, and quoted passages remain the property of their respective publishers.
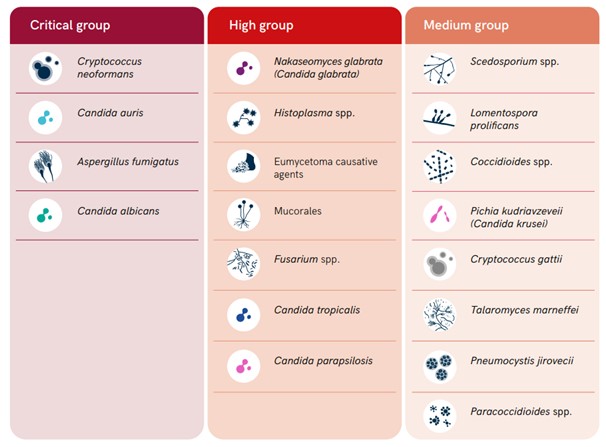
Figure 1 is reproduced from the World Health Organization fungal priority pathogens list (2022), p. 6, with the source cited beneath the figure.
Please see the Disclaimer at the end of this page for more information.
© 2026 Medical Education Network. All rights reserved.
Why Fungal Pathogens, and Why Now
Multi-drug-resistant bacterial strains are responsible for 1.27 million deaths annually and are estimated to indirectly contribute to 4.95 million deaths. Considerable resources have been directed towards the research into, and management of, these infective pathogens.5 (p. vii)
Recently, however, the World Health Organisation (WHO) and other infectious disease watchdogs have noted, with concern, the alarming global increase in cases of multi-resistant infectious fungal diseases, or IFDs.
Unlike bacterial infections, IFDs have to date received very little attention. To address this, in 2022 the WHO released the first fungal priority pathogens list — the WHO FPPL. The report lists 19 fungal pathogens as priority pathogens and differentiates between those with a critical, medium and high risk (see Figure 1).
Against this background, alarm bells have been sounded regarding the rapid increase of Candida auris (C. auris), an emerging fungal infective listed in the critical group in the FPPL. In the US alone, cases of C. auris have risen by almost 200% since 2019.2 While global data is scanty, it is thought that this situation is playing out in countries across the globe, including here in South Africa.
What We Know So Far
C. auris produces invasive candidiasis of the blood (candidaemia), internal organs, cardiovascular, central nervous and urinary tract systems. It also is known to cause infections of the bone and eye.5 (p. 16)
Patients most at risk are hospitalised patients — particularly those in critical care situations — and immunocompromised patients, including those with underlying severe diseases such as diabetes, TB, in particular those with previous mycosis infections, HIV patients and patients with haematologic malignancies.5 (p. 16)
Drug Resistance Profile
The pathogen is intrinsically resistant to most available antifungal medications, and some strains are pan-resistant. A 2019 paper published in JAMA indicates the pathogen is:
Mortality and Morbidity
There is a high mortality rate in cases of C. auris infections, ranging from 29% to 53%.5 (p. 16) According to the WHO:
Furthermore, they indicate that whilst the actual rate of global infection is difficult to determine due to a lack of studies:
Therapeutic Controls and Management
C. auris has a high person-to-person transferral rate, particularly within hospitals and care facilities. Its ability to form biofilms and adhere to polymeric surfaces means that normal bio-cleaning agents are frequently ineffective. The pathogen may persist on shared equipment and other surfaces if care is not taken.4, 3 (p. 2036)
This means the potential for outbreaks is high, and eradicating the pathogen is extremely difficult. The implications for hospitals, clinics and nursing homes are significant, as eradication may require shutting down wards and facilities.5 (p. 1)
What We Know in South Africa
The first case of Candida auris was identified in 2009. It was confirmed retrospectively in 2014 from a sample initially incorrectly identified as Candida haemulonii.3 (p. 2036)
This misidentification illustrates one of the complexities regarding the control of C. auris, namely how difficult it is to identify using standard biochemical laboratory tests.3 (p. 2038) The implications of these difficulties for resource-constrained environments, such as in South Africa and other developing countries, are concerning. Furthermore, it could imply that the number of cases is actually much higher than reported.
In their 2019 paper which looked into the epidemiological shifts occurring in candidaemia driven by C. auris, researchers van Schalkwyk et al. reported that the pathogen was responsible for more than 10% of all reported candidaemias, making it the third most commonly occurring Candida species in South Africa.4 This increase in cases denotes a clear shift in the epidemiology observed from the previous national survey conducted between 2009–2010.4
In 2018 Govender et al. published the results of their comprehensive national survey of C. auris cases, conducted over four years (October 2012–November 2016). They reviewed 1,692 cases and determined that the local C. auris clade is unique, separate from the Asian, South Asian and South American clades, indicating that it emerged independently in Africa.3 (p. 2036)
Of the cases they detected, the overwhelming majority — 93% — were found in the private sector, and 92% were located in Gauteng Province.3 (p. 2036) van Schalkwyk et al. indicated a similar distribution of cases.4 Several reasons for this demographic concentration were given, including a more mobile population rate and a higher referral rate within the province.4
van Schalkwyk further determined that:
In Conclusion
C. auris is difficult to detect in a resource-constrained environment, difficult to treat due to its properties and antimicrobial resistance profile, and extremely difficult to eradicate from hospitals, clinics and care facilities once it has become endemic.
As it reshapes the candidaemia profile, this priority pathogen poses a significant threat.
Given the rapid rise in cases, prefaced against the ongoing battle with antimicrobial overprescribing, poor prescribing practices, and inadequate infection control practices, the question arises: will we be able to stem the march of this priority pathogen before it becomes yet another lethal endemic resident in our hospitals and communities?
References
- Bradley, S. F. (2019). What is known about Candida auris. JAMA, 322(15), 1510–1511. https://doi.org/10.1001/jama.2019.13843
- Centers for Disease Control and Prevention. (2022). Candida auris. https://www.cdc.gov/fungal/candida-auris/index.html
- Govender, N. P., Magobo, R. E., Mpembe, R., Mhlanga, M., Matlapeng, P., Corcoran, C., Govind, C., Lowman, W., Senekal, M., & Thomas, J. (2018). Candida auris in South Africa, 2012–2016. Emerging Infectious Diseases, 24(11), 2036–2040. https://doi.org/10.3201/eid2411.180368
- van Schalkwyk, E., Mpembe, R. S., Thomas, J., Shuping, L., Ismail, H., Lowman, W., Karstaedt, A. S., Chibabhai, V., Wadula, J., Avenant, T., Messina, A., Govind, C. N., Moodley, K., Dawood, H., Ramjathan, P., Govender, N. P., & GERMS-SA. (2019). Epidemiologic shift in candidemia driven by Candida auris, South Africa, 2016–2017. Emerging Infectious Diseases, 25(9), 1698–1707. https://doi.org/10.3201/eid2509.190040
- World Health Organization. (2022). WHO fungal priority pathogens list to guide research, development and public health action. World Health Organization. https://www.who.int/publications/i/item/9789240060241
Disclaimer & Fact-Checking Policy
Disclaimer. This article is compiled from a variety of resources researched and compiled by the contributor. It is in no way presented as an original work. AI may have been used to assist in preparing this article. Every effort has been made to correctly attribute quotes and content. Where possible, all information has been independently verified. The Medical Education Network bears no responsibility for any inaccuracies which may occur from the use of third-party sources. The Medical Education Network urges all practitioners to review the original material as their clinical reference. If you have any queries regarding this article contact us
Fact-checking Policy. The Medical Education Network makes every effort to review and fact-check the articles used as source material in our summaries and original material. We have strict guidelines in relation to the publications we use as our source data, favouring peer-reviewed research wherever possible. Every effort is made to ensure that the information contained here accurately reflects the original material. Should you find inaccuracies or out-of-date content or have any additional issues with our articles, please make use of the Contact Us form to notify us.

